


Ankle Pain Ultrasound Scan Explained
A swollen ankle after a run, a sharp pain at the front of the joint when walking downstairs, or a nagging ache that never quite settles – these symptoms often raise the same question: what is actually causing it? An ankle pain ultrasound scan can help answer that question during assessment, rather than relying on guesswork or waiting to see whether symptoms change.
For many patients, the difficulty is not simply pain. It is uncertainty. Ankles are complex structures, and several problems can produce very similar symptoms. A strained ligament, an irritated tendon, a joint lining problem or a small area of fluid can all feel broadly alike in the early stages. That is why imaging, when clinically indicated, can be so useful. It allows the structures that commonly cause ankle pain to be assessed in real time and matched against the findings from a hands-on examination.
What an ankle pain ultrasound scan can show
Ultrasound is particularly useful for soft tissue structures around the ankle. These include tendons, ligaments, joint capsules, bursae and areas of inflammation or fluid. If the pain sits around the outer ankle, for example, the scan may help assess the peroneal tendons and the lateral ligament complex. If the pain is more central or at the front of the ankle, it may help identify joint irritation, synovitis or impingement-related changes.
It can also be helpful for problems at the inner ankle, where the tibialis posterior tendon, deltoid ligament and nearby soft tissues may all need to be assessed carefully. Around the back of the ankle, ultrasound can often show changes involving the Achilles tendon or the tissues nearby. In the right clinical setting, it can also identify tendon thickening, partial tears, sheath inflammation and abnormal fluid collections.
What ultrasound does less well is assess bone in fine detail. If a fracture, significant joint surface injury or deeper bony problem is suspected, an X-ray or MRI may be more appropriate. This is where good clinical judgement matters. The aim is not to scan everyone automatically. It is to use the right test at the right point in the diagnostic process.
Why examination still matters before an ankle pain ultrasound scan
An ultrasound scan is most useful when it forms part of a structured assessment. Symptoms alone rarely tell the full story. A clinician will usually want to know how the pain started, whether there was a twist or impact, how quickly swelling developed, what movements reproduce symptoms and whether the problem is improving, worsening or recurring.
The physical examination then helps narrow the possibilities. This may include checking tenderness, swelling, range of movement, ankle stability, tendon loading and walking pattern. The scan can then be used to confirm, refine or occasionally challenge the initial working diagnosis.
This matters because imaging without context can be misleading. Some people have tendon thickening or minor ligament changes on scan but little relation between those findings and their actual pain. Equally, a scan may look quite subtle while the clinical picture clearly points to an active injury that needs treatment. Diagnosis works best when the scan supports the assessment rather than replacing it.
Common ankle problems ultrasound may help identify
One of the most common reasons for ankle pain is ligament injury after a twist. In some cases, the ankle improves steadily with time and rehabilitation. In others, pain lingers, swelling returns with activity or the joint still feels unstable weeks later. Ultrasound may help assess whether the lateral ligaments remain thickened, disrupted or tender in a way that matches the ongoing symptoms.
Tendon problems are another frequent reason for scanning. The peroneal tendons on the outside of the ankle can become irritated after overuse or instability. Tibialis posterior problems on the inside of the ankle can affect walking mechanics and arch control. The Achilles, although often thought of separately, may also contribute to pain that spreads into the rear ankle. Ultrasound is well suited to assessing tendon structure and how the tendon moves during dynamic testing.
Ankle joint inflammation can also be seen in some cases, especially where there is excess fluid or thickening of the synovial lining. For patients with pain at the front of the ankle, impingement syndromes may be part of the picture, particularly if symptoms are worse in certain positions or during sport. Ultrasound can sometimes help highlight soft tissue crowding or inflamed tissue in the symptomatic area.
There are, however, limits. Osteochondral injuries, deep cartilage problems and some causes of persistent ankle locking or catching may require MRI instead. If symptoms suggest something beyond the reach of ultrasound, that should be explained clearly.
What happens during the scan
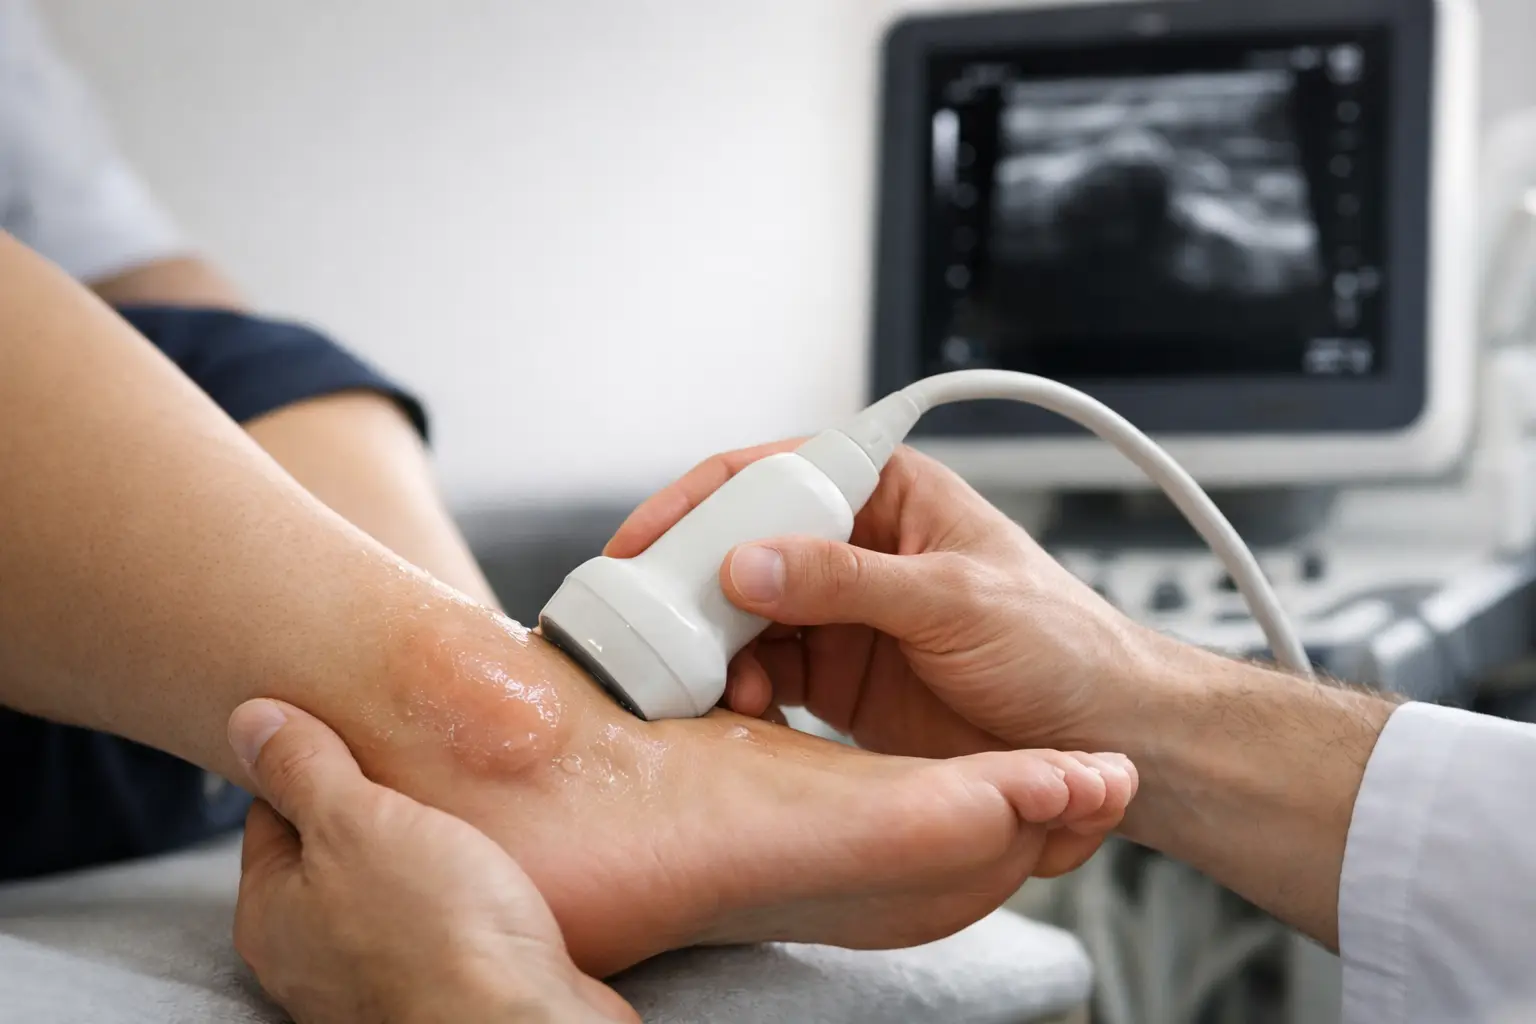
The scan itself is straightforward. Gel is applied to the skin and a handheld probe is moved over the painful area and surrounding structures. Unlike some forms of imaging, ultrasound allows the ankle to be examined dynamically. That means structures can be viewed while the foot is moved, tendons are loaded or the area of pain is reproduced.
This dynamic element is one of ultrasound’s real strengths. A tendon that appears reasonable when still may show abnormal movement when the ankle turns. A painful structure can often be assessed directly while the patient points to the exact spot that hurts. That level of correlation between symptoms, examination and imaging is often difficult to achieve with static imaging alone.
The scan is generally quick, and the findings can usually be discussed immediately. For patients, that often changes the experience from uncertainty to clarity. Instead of being told to simply rest and wait, they can understand which structure is involved, how significant the issue appears and what the next step is likely to be.
How scan findings guide treatment
The value of an ultrasound scan lies in what it changes. If the findings show a mild tendon irritation without tearing, treatment may focus on load management, footwear advice, targeted rehabilitation and a staged return to activity. If a ligament injury is still active and the ankle remains unstable, the plan may place more emphasis on support, strengthening and proprioceptive work.
Where inflammation is more pronounced, imaging may also help determine whether further treatment is appropriate. In some cases that may include orthotic intervention, hands-on treatment, rehabilitation planning or injection therapy, but only where the diagnosis and overall clinical picture support it. The aim is not to move straight to a procedure. It is to choose treatment that fits the structure involved, the severity of the problem and the patient’s activity goals.
This is particularly important for persistent or recurrent ankle pain. If a patient has already tried rest, online exercises or general advice without success, the missing piece is often diagnostic accuracy. A better understanding of the tissue involved can prevent weeks of ineffective treatment.
When an ankle pain ultrasound scan is most useful
A scan is often worth considering when ankle pain has not settled as expected, when the diagnosis is unclear, or when treatment decisions depend on identifying the exact structure involved. It can also be helpful for patients who have recurring sprains, ongoing swelling, suspected tendon injury or pain that keeps returning with sport or longer walks.
It may be less useful when symptoms are already improving in a predictable way and the examination clearly supports a simple minor sprain. Equally, if the pattern suggests a fracture or deeper joint problem, another imaging route may be more suitable from the outset. This is why a consultation-led model tends to work better than treating ultrasound as a standalone product. The decision to scan should come from assessment, not from assumption.
At South London Foot Clinic, that principle sits at the centre of care. Patients are assessed first, scanned where appropriate and then talked through the findings in plain language so the treatment plan makes sense.
What patients should expect after the appointment
Most patients want the same thing after assessment: a clear explanation and a realistic plan. That means understanding what the scan has shown, what it has ruled out, how long recovery may take and what needs to happen next. Some conditions settle relatively quickly with the right management. Others need a more gradual rehabilitation process and better load control.
It also helps to be realistic about what imaging can and cannot do. A scan does not heal the ankle. It improves diagnostic confidence. That can shorten the path to appropriate treatment, but recovery still depends on the nature of the injury, the patient’s general health, activity demands and how well the plan is followed.
For anyone dealing with ankle pain, the most useful next step is not always more treatment straight away. Sometimes it is getting a proper answer first. Once the cause is clear, decisions become easier, treatment becomes more precise and recovery tends to feel far less uncertain.
A good assessment should leave you knowing where the pain is coming from, what can be done about it and what progress should realistically look like over the next few weeks.



