


Ankle Injection Treatment Review for Lasting Relief
An ankle injection treatment review should not start with the injection itself. It should start with the reason your ankle hurts. Persistent pain after a twist, recurring swelling after activity, pain on stairs, or stiffness that limits walking can all feel similar, yet arise from very different structures. Treating the wrong structure may provide little benefit and can delay the rehabilitation that would make the real difference.
For some patients, an injection is a useful, carefully targeted part of treatment. For others, it is not appropriate, or it needs to be paired with changes to footwear, orthotic support, activity modification and rehabilitation. A thorough assessment makes that distinction clear.
What an ankle injection treatment review should assess
The ankle is a compact, complex area. Pain may be coming from the ankle joint itself, a tendon sheath, a ligament, the joint lining, the cartilage, or a neighbouring structure such as the subtalar joint or sinus tarsi. The location of pain alone does not always give a reliable answer.
A clinical review should therefore consider how the symptoms began, what movements reproduce them, whether there is swelling or instability, and how the problem affects work, sport and daily walking. Previous ankle injuries matter. A sprain that seemed to settle years ago can leave altered joint movement, ligament laxity or early degenerative change that becomes more noticeable over time.
Why diagnosis comes before treatment
An injection can reduce inflammation and pain in the right circumstances, but it cannot repair a torn ligament, correct poor loading mechanics or resolve every form of tendon pain. If there is a significant injury, a stress fracture, infection, inflammatory arthritis or a circulation concern, the treatment pathway may be entirely different.
At South London Foot Clinic, diagnostic ultrasound may be used where clinically indicated as part of the consultation. It can help assess soft tissues, fluid around a joint or tendon, and some structural changes in real time. This supports a consult, scan, discuss, treat approach, rather than making assumptions based on symptoms alone.
Ultrasound does not replace every form of imaging. X-ray, MRI, blood tests or onward referral may sometimes be more suitable. The value lies in selecting the investigation that answers the clinical question, not in scanning every painful ankle as a routine step.
When ankle injections may be considered
Injection treatment may be considered when pain has persisted despite appropriate initial care, or when inflammation is preventing meaningful progress with rehabilitation. It is usually one option within a wider treatment plan, not a stand-alone cure.
Common situations where an injection may be discussed include ankle joint synovitis, osteoarthritis-related pain, certain forms of ankle impingement, inflammation around a tendon sheath, or pain arising from a nearby joint. The precise diagnosis matters because the medication, injection site and expected outcome differ between these conditions.
For example, a patient with inflammatory joint lining and recurrent swelling may gain short-term relief that allows them to restore movement and strength. Someone with established ankle arthritis may experience improved comfort for a period, but still need practical support with footwear, load management and exercise. If pain is caused primarily by mechanical instability, an injection may be of limited value unless the underlying instability is also addressed.
Types of injection and what they are intended to do
The most appropriate medication depends on the structure being treated and your medical history. A corticosteroid injection is commonly used to settle inflammation. It may be combined with local anaesthetic, which can provide immediate short-lived pain relief and sometimes offers useful diagnostic information about the source of symptoms.
Corticosteroid can be very effective for selected inflammatory conditions, but its effects are not always permanent. It is not generally used repeatedly without careful review, particularly around tendons or in weight-bearing joints. Repeated injections can carry greater risk to local tissues, so the decision should be based on response, diagnosis and the alternatives available.
Viscosupplementation, often involving hyaluronic acid, may be discussed for some joint-related symptoms, particularly where osteoarthritic change is contributing to pain and stiffness. Its suitability and likely benefit vary from person to person. It is not a replacement for cartilage, and expectations should remain realistic.
The aim is not simply to make the ankle temporarily quieter. The aim is to create a window in which you can move more comfortably, follow a rehabilitation plan and return to appropriate activity with better control of the underlying problem.
Benefits, limitations and risks
A successful injection may reduce pain, swelling or stiffness enough to improve walking, sleep, work and exercise tolerance. It can also help clarify whether a particular joint or soft-tissue structure is the key pain generator. For an active person who has been unable to progress with strengthening because every step is painful, this can be clinically useful.
However, results vary. Some people improve substantially, some only briefly, and some not at all. The duration of benefit depends on the condition being treated, the severity of tissue change, daily loading and whether rehabilitation addresses contributing factors. An injection should not be viewed as permission to immediately return to high-impact activity at full intensity.
Potential side effects should be discussed before you consent to treatment. These can include temporary post-injection soreness, bruising, skin colour change or thinning at the injection site, a short-term rise in blood glucose for people with diabetes, and a flare of pain in the first few days. Infection is uncommon but serious. Tendon weakening or rupture is also a concern with corticosteroid in certain locations, which is why accurate diagnosis, technique and aftercare matter.
You should tell your clinician about diabetes, blood-thinning medication, allergies, pregnancy, immune suppression, previous reactions to injections and any current illness or skin infection. These details can affect whether treatment is suitable or whether it should be postponed.
What happens during an ultrasound-guided ankle injection
If an injection is recommended, the clinician should explain the diagnosis, intended medication, likely benefits, relevant risks and alternatives. You should have the opportunity to ask questions and decide whether to proceed. Consent is not a formality – it is part of making a treatment decision that fits your circumstances.
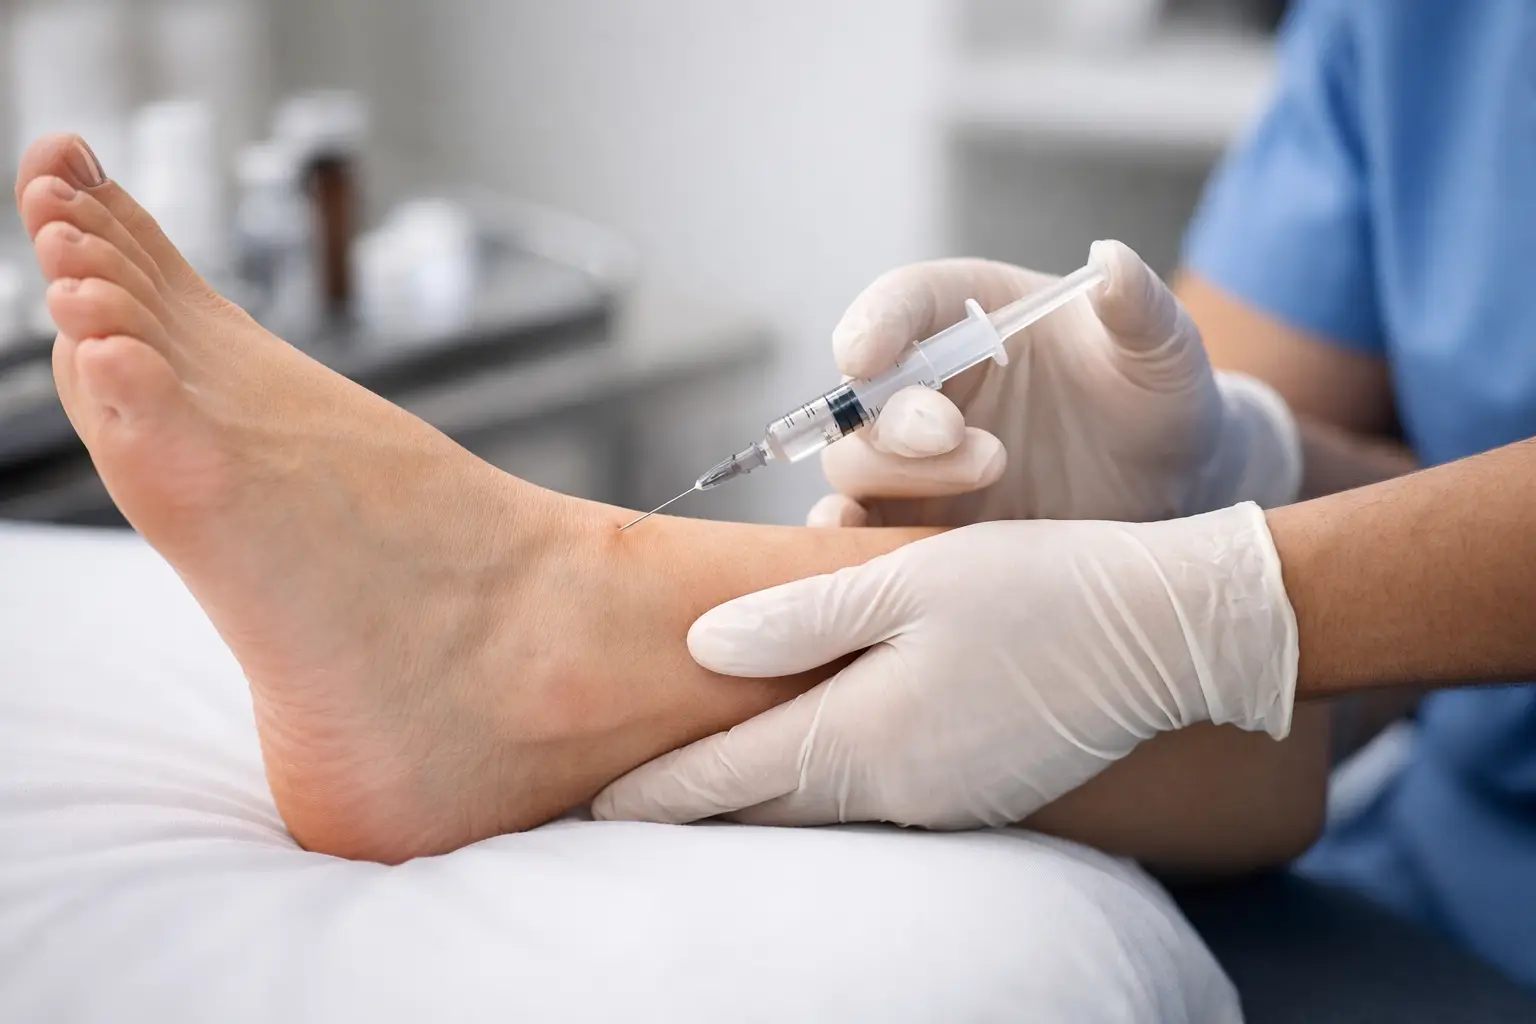
The skin is cleaned using an aseptic technique. Ultrasound guidance may be used to identify the target structure and guide needle placement in real time. This is particularly valuable in the ankle, where joints, tendons, blood vessels and nerves sit close together. It helps the clinician place the medication where it is intended to work.
Most injections are brief. You may feel pressure or a short sharp sensation, followed by temporary numbness if local anaesthetic is used. The ankle may initially feel better than expected because of the anaesthetic, so it is sensible not to test it with a long run, gym session or demanding shift immediately afterwards.
Recovery after an ankle injection
Aftercare depends on the diagnosis and injection site, but a short period of relative rest is commonly advised. Gentle day-to-day walking is often appropriate, while impact activity, heavy lifting and intense exercise may need to wait for a few days or longer. Your clinician will give advice matched to your treatment rather than a generic timetable.
A mild ache for 24 to 48 hours can occur. Applying a wrapped cold pack for brief periods and using suitable pain relief, if advised, may help. If you have diabetes, monitor your blood glucose more closely following a steroid injection, as levels can rise temporarily.
Contact the clinic or seek urgent medical advice if you develop increasing redness, heat, marked swelling, fever, feeling unwell, severe pain that does not settle, or new loss of sensation. These symptoms are not expected and need prompt assessment.
Rehabilitation remains central after the injection. Depending on the cause of pain, this may include restoring ankle movement, calf strength, balance, landing control, footwear changes or custom orthotic support. Returning gradually to running or court sport is usually more reliable than relying on pain relief alone.
Making a confident decision
The right question is not simply, “Will an injection fix my ankle?” A more useful question is, “What is causing my ankle pain, and would an injection improve my ability to recover?” The answer should be based on a structured assessment, a clear explanation of the findings and an honest discussion about expected results.
If ankle pain is persisting, recurring or limiting the activities that matter to you, seek assessment before choosing a treatment. A diagnosis-led plan gives you the best basis for deciding whether an injection is the right next step, or whether another approach offers a stronger route back to comfortable movement.



