


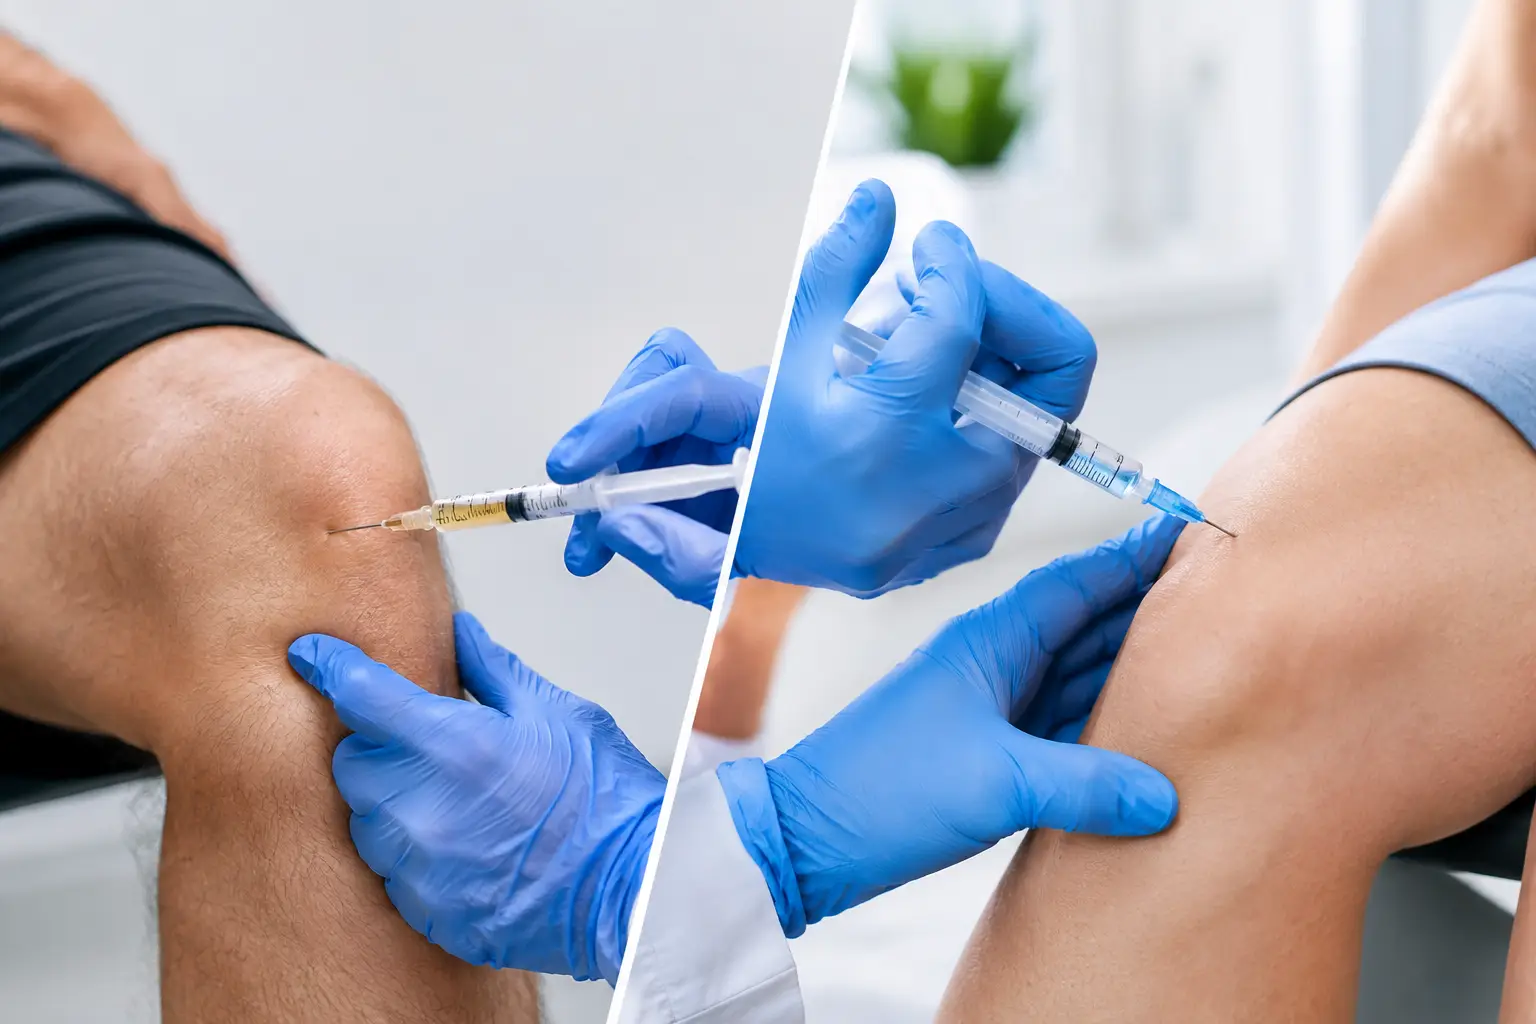
Steroid Injections Versus Viscosupplementation
A painful joint can make walking, exercise and even choosing footwear feel difficult. When simpler measures have not settled symptoms, the discussion may turn to steroid injections versus viscosupplementation. Both treatments can have a place in managing joint pain, but they work differently, suit different clinical situations and should only follow a clear diagnosis.
At South London Foot Clinic, an injection is not treated as a generic answer to pain. The priority is to establish which structure is causing symptoms, assess the joint and surrounding soft tissues, and discuss whether an injection is likely to provide worthwhile benefit alongside a wider recovery plan.
Steroid injections versus viscosupplementation: the key difference
A steroid injection contains corticosteroid medicine, often combined with local anaesthetic. Corticosteroid reduces inflammation within or around a joint. It may be considered where pain is being driven by an inflamed joint lining, arthritis flare, synovitis or irritation in a specific soft-tissue structure. The local anaesthetic can sometimes provide short-term relief and may also offer useful diagnostic information.
Viscosupplementation involves injecting hyaluronic acid into a joint. Hyaluronic acid is a naturally occurring component of joint fluid. The aim is not to suppress inflammation in the same way as steroid, but to improve the lubrication and shock-absorbing properties of the joint environment. It is most commonly discussed for osteoarthritis.
Put simply, steroid injections are generally used to calm inflammation. Viscosupplementation is intended to support the joint's mechanical environment, particularly where degenerative change is contributing to pain. Neither treatment repairs worn cartilage, and neither removes the need to address load, footwear, strength, movement patterns or other factors maintaining the problem.
Why the diagnosis comes before the injection
Foot and ankle pain is not always caused by the joint that feels painful. Pain at the front of the ankle, for example, may relate to arthritis, impingement, a tendon problem, instability or referred pain. Pain around the big toe may be due to osteoarthritis, a joint capsule irritation, a stress injury or a nerve-related condition. These conditions require different management.
A detailed consultation helps identify the pattern of symptoms: when pain began, what aggravates it, whether there is stiffness or swelling, and how it affects work, sport and daily activity. Clinical examination assesses movement, tenderness, joint stability and how the foot functions under load. Diagnostic ultrasound may be used when it is clinically indicated to examine accessible joints, tendons, bursae and other soft tissues.
Ultrasound can also support accurate placement for certain injections. However, it is not a replacement for clinical reasoning, and it does not show every structure equally well. Sometimes other imaging, a referral or a different treatment approach is more appropriate. A clear explanation of these limits is part of safe care.
When a steroid injection may be considered
Steroid injection can be useful when inflammation is a significant part of the presentation and symptoms have not improved sufficiently with appropriate non-invasive treatment. For some patients, reducing pain and inflammation creates a more realistic opportunity to restore movement, begin rehabilitation or return gradually to activity.
The speed of effect varies. Local anaesthetic, when used, may settle pain for a few hours. Steroid itself may take several days to begin working, and some people experience a temporary increase in pain for a short period afterwards. Relief can last weeks or months, but this is unpredictable. Some patients obtain substantial improvement; others have only limited or short-lived benefit.
Steroid is not automatically the best choice for every painful joint. Repeated injections in the same area require careful consideration. Depending on the tissue and clinical context, corticosteroid can affect tendon health, skin colour or fat padding, and it may not be appropriate where there is concern about infection, fracture or certain medical conditions. People with diabetes may experience a temporary rise in blood glucose after a steroid injection and should plan monitoring with their usual healthcare professional.
A steroid injection should therefore have a defined purpose. It may help settle an acute inflammatory flare, reduce pain enough to progress rehabilitation or clarify whether a particular structure is contributing to symptoms. It should not be presented as a permanent cure for a mechanical or degenerative problem.
When viscosupplementation may be considered
Viscosupplementation is more likely to enter the discussion when assessment suggests osteoarthritis within a joint, particularly where stiffness, activity-related pain and reduced joint tolerance are persistent features. The response is usually less immediate than with local anaesthetic and steroid. Some people notice gradual improvement over several weeks, while others do not find it helpful.
Evidence for viscosupplementation is strongest in some larger arthritic joints, especially the knee. Its role in smaller foot and ankle joints is less established, and outcomes can vary considerably with the joint involved, the degree of arthritis and the individual's overall loading demands. This does not mean it can never be considered, but it does mean expectations must be realistic and the rationale should be specific.
For a person with painful ankle arthritis who wants to continue walking, working or exercising, viscosupplementation may be discussed as one option within a conservative management plan. That plan may also include footwear changes, activity modification, targeted exercises, orthoses or referral where needed. If there is advanced joint damage, marked deformity or progressive loss of function, an injection alone may not be enough to deliver meaningful long-term improvement.
Benefits and limitations to weigh up
The right choice is rarely about which injection is generally ‘better’. It is about the nature of the pain and what a treatment can reasonably achieve.
Steroid may be the more logical option when inflammation is prominent and a quicker reduction in symptoms is needed. Its limitation is that benefits can fade, and it does not alter the underlying joint degeneration or biomechanical demands. Viscosupplementation may appeal where osteoarthritis is the main issue and the aim is to improve joint comfort over time without using corticosteroid. Its limitation is more variable evidence in the foot and ankle, a slower onset and no guarantee of response.
Both procedures carry potential risks. These include post-injection pain, bruising, bleeding, skin changes, allergic reaction and, rarely, infection. The risk of infection is low but serious, which is why sterile technique and appropriate patient selection matter. You should be given clear aftercare advice, including which symptoms require urgent medical attention.
An injection is also not suitable when there is an active local or systemic infection. Blood-thinning medication, diabetes, inflammatory arthritis, previous surgery and relevant allergies should all be discussed beforehand. If symptoms are severe, unexplained or associated with red flags such as a hot swollen joint, fever, sudden inability to bear weight or significant trauma, urgent medical assessment may be required rather than routine injection treatment.
What treatment should look like after an injection
The period after an injection matters as much as the procedure itself. A short reduction in activity may be advised, followed by a planned return to normal loading. The exact guidance depends on the joint treated, the reason for the injection and the activities you need to return to.
Pain relief can create a useful treatment window, but it can also encourage people to do too much too soon. If running, long shifts on your feet or poorly supportive footwear contributed to the original problem, these factors need addressing. Rehabilitation may focus on joint mobility, calf and foot strength, balance, gait or progressive return to sport. Orthoses may be appropriate for some patients, but only where they match the clinical findings and treatment goal.
Follow-up provides an opportunity to assess whether the expected response has occurred. If it has not, the diagnosis and plan should be reviewed rather than simply repeating the same intervention. Persistent pain sometimes needs further investigation, a change in rehabilitation strategy or referral to another specialist.
Making a confident decision
A useful injection consultation should leave you knowing what is believed to be causing your pain, why a particular injection is being considered, what improvement is realistic and what happens if it does not help. You should also understand the alternatives, which may include rehabilitation, orthoses, medication discussion with your GP, further imaging or specialist referral.
The most helpful next step is not to choose an injection from a menu. It is to obtain a structured assessment that identifies the painful structure and builds a practical plan around how you need your foot or ankle to function.



